The radial nerve lifts the wrist and fingers and carries feeling from the back of the hand. When it is injured, the wrist drops, the grip loses power and letting go becomes as hard as holding on.
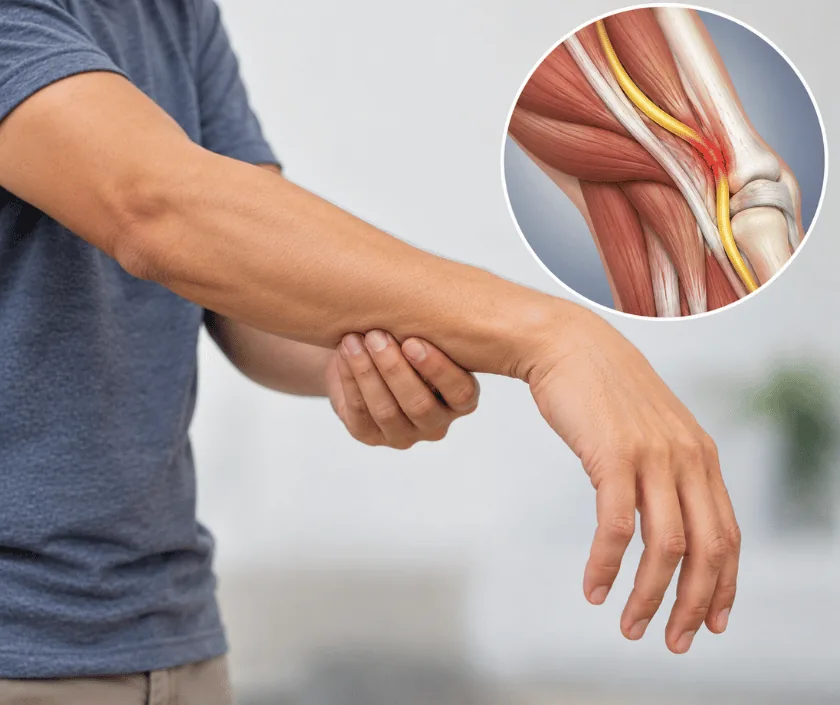
Radial nerve injury damages the nerve that spirals around the upper arm bone and opens the hand. The classic sign is a dropped wrist, where the wrist and fingers cannot be lifted against gravity. Some injuries recover on their own with splinting and therapy. Others need the nerve repaired, grafted or, later, a tendon transfer.
The radial nerve leaves the shoulder and winds around the back of the upper arm bone in a shallow groove before crossing the elbow into the forearm. That course explains a lot. A break in the middle of the upper arm can bruise or trap the nerve where it lies against bone, which is why some patients notice a limp wrist only after their fracture has been treated.
Its work is to open the hand. Muscles supplied by the radial nerve lift the wrist, straighten the fingers at the knuckles and pull the thumb outwards. Feeling comes from the back of the forearm, the back of the hand and the web between thumb and index finger. Bending the fingers is left to other nerves, so a person with radial palsy can still make a weak fist once the wrist is supported.
Not every radial injury needs surgery. When the nerve is bruised but still in one piece, recovery often begins by itself over weeks to months, helped by a splint that holds the wrist up. Where the nerve has been cut or is trapped in a fracture site, repair is needed.
Surgery is considered when the nerve is known to be cut, when it is trapped at a fracture site, or when months pass with no sign of recovery.
Muscle power is graded and feeling mapped, often more than once, to see whether the nerve is already recovering. Nerve studies help decide whether to wait or to operate.
The arm is numbed with a block and sedation offered. Your incision follows the nerve where it winds around the arm bone or crosses the elbow, keeping the field bloodless.
Scar tissue and fracture callus around the nerve are cleared under magnification. Sometimes freeing the nerve is the whole operation, if it is intact but tethered.
Cut ends are trimmed to healthy tissue and joined with fine sutures. If they will not meet without tension, a segment of spare sensory nerve is used to bridge the gap.
The wound is closed and a splint holds the wrist up so tendons stay at working length. A therapy schedule is set out before you go home.
The arm is elevated and rested in the splint. Pain is usually modest and controlled with simple medication. Fingers are moved gently as instructed.
Dressings and sutures are reviewed. A therapist fits a working splint that supports the wrist while allowing the fingers to be used.
Light activity resumes with the splint on. Muscle power has usually not returned yet, which is expected at this stage of nerve regrowth.
Wrist lift often appears before finger and thumb movement. Progress continues slowly, and if power does not return a tendon transfer can be discussed.
Outcomes vary with the cause. A bruised nerve after a fracture often recovers well without surgery, while a divided nerve repaired late recovers less predictably. Wrist lift usually returns before finger and thumb movement, and some patients regain enough for daily tasks without reaching their earlier strength. Where power does not return within a reasonable time, tendon transfer offers another route to a working hand. Recovery can vary considerably between people.
Nerve surgery on the arm is generally safe, though you should understand the risks before agreeing to it.
Splinting is the heart of home care here, because it keeps the hand usable while the nerve regrows.
In radial palsy the tendons are usually intact. They simply have no nerve signal reaching the muscles that pull them.
Nerve fibres advance slowly, so a month is far too early to judge. Many bruised nerves take several months to show their first movement.
Nerves bruised by a fracture often recover on their own. Operations are reserved for cut nerves, trapped nerves and cases that fail to progress.
The splint holds the wrist in a working position, protects tendon length and lets you keep using the hand while the nerve recovers.
Radial nerve cases at Elegance Clinic in Surat are followed over time, because deciding when to wait and when to operate is as important as the surgery itself.

Cost for radial nerve surgery depends on whether the nerve simply needs freeing, whether a graft is required and how long the operation and hospital stay run. Splints and therapy sessions also form part of the total. A written estimate is prepared after your examination, covering surgery, anaesthesia, hospital charges and planned review visits. Where the injury followed a road accident or an incident at work, insurance or employer cover may apply and the team will guide you through it.
These are the questions that come up most often in consultation. If yours is not here, send it on WhatsApp and the team will reply, usually the same day.
Ask your question →Charges depend on whether the nerve needs freeing, repairing or grafting, and on theatre and hospital time. Splints and therapy add to the total. A written estimate is given after examination so you can plan before any date is booked.
Operating on the radial nerve is well established and usually done under a block that numbs the arm. Infection, stiffness and partial recovery remain possible, and these are discussed with you honestly before consent is taken.
Skin heals within a fortnight, but nerve recovery is measured in months. Fibres travel slowly down the arm, and wrist lift usually returns before the fingers and thumb. Judging the final result often takes a year or more.
Many patients regain useful wrist and finger extension, particularly when the nerve was bruised rather than cut. Results after late repair are less predictable. When power does not return, tendon transfer can restore a working hand by another route.
No. A nerve bruised by a fracture often recovers with a splint, therapy and time. Surgery is reserved for nerves that have been cut, nerves trapped in a fracture, and cases showing no progress after watchful review.
Clean cuts are best repaired early, within days, while the ends stay healthy. Closed injuries are usually watched for a period first, then operated on if testing shows no recovery, since waiting too long allows muscles to waste.
Each muscle group is graded and areas of numbness mapped, then compared with earlier findings if you have been seen before. Nerve studies may be arranged. Options, timing and a written estimate are explained before you decide.
Seeing patients from across the city and beyond: read about the practice on the plastic surgeon in Surat page, or check what a written estimate covers on the costs and insurance page.
