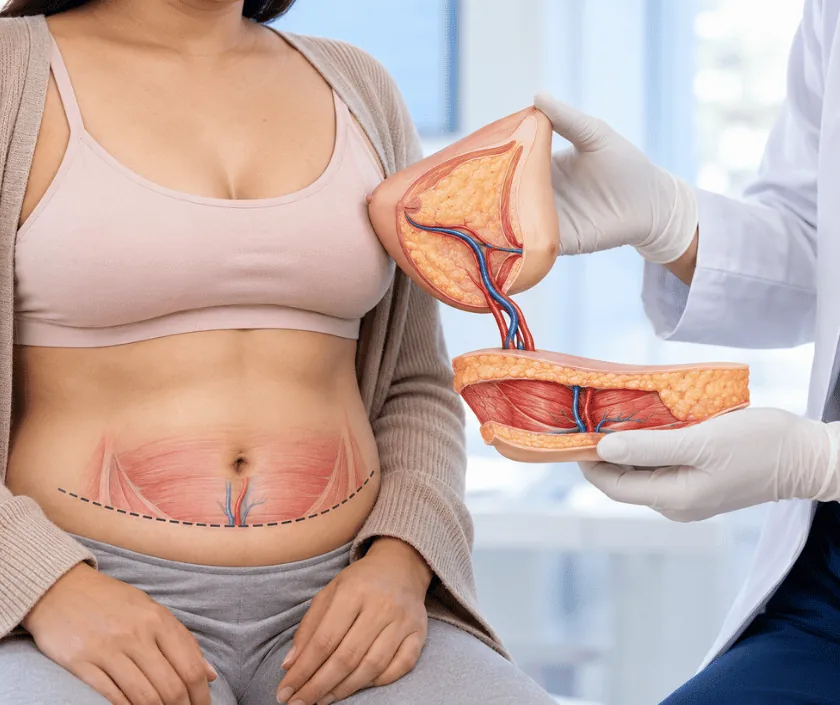
Rebuilding the breast after mastectomy, with implants or your own tissue, immediately or years later, on your timeline.
Women planning mastectomy or living after one, and women with asymmetry after breast conservation.
Review of the oncology plan, examination, and an honest discussion of implant versus own tissue options.
Microscope equipped theatre for flap reconstruction, coordinated with the breast cancer team.
Reconstruction after mastectomy is generally payable under mediclaim.
Nothing here is improvised. The sequence below is how care in this specialty is actually organised, and your own written plan follows it.
Reconstruction is discussed before cancer surgery, immediate reconstruction is often possible in the same operation.
An implant, an expander or your own tissue rebuilds the breast mound, chosen with you, not for you.
The other breast is adjusted where wanted, and the nipple reconstructed or tattooed as a final stage.
Reconstruction does not interfere with cancer follow up, and imaging continues as your oncologist plans.
"Reconstruction is not vanity. It is the last stage of treating the cancer."
Every option, implant, expander or your own tissue, has honest trade offs in scars, recovery and feel, discussed openly before you choose.
Timing is flexible: immediate reconstruction at mastectomy, or delayed reconstruction months or years later, both give good results.

Published with documented patient consent, generalised for age and sex, in line with advertising norms applicable to medical practitioners in India.
Published bands are for Surat and include surgeon, anaesthesia, theatre and standard stay. Where a band is not published, a written estimate follows examination. Cover under mediclaim and schemes is confirmed before admission.
Ask for an estimate →These are the questions that come up in consultation most often. If yours is not here, send it on WhatsApp and the team will reply, usually the same day.
Ask your question →Often yes. Immediate reconstruction avoids a second major operation and waking without a breast mound. Whether it is advisable depends on the cancer plan, especially radiotherapy, and is decided with the oncology team.
Neither is better for everyone. Implants mean shorter surgery and recovery; your own tissue feels more natural and ages with you but adds a donor scar. The honest trade offs are discussed before you choose.
No. Reconstruction does not interfere with examination or imaging follow up, and surveillance continues exactly as your oncologist plans.
Commonly one to three stages: the main reconstruction, an adjustment for symmetry if wanted, and nipple reconstruction or tattooing. Some women choose to stop after the first stage.
Reconstruction after mastectomy is generally payable under mediclaim as part of cancer treatment. Pre authorisation is raised before admission.
Sensation is usually reduced after mastectomy and reconstruction, and it recovers only partly over time. Shape, softness and symmetry are what reconstruction sets out to restore, and this is discussed openly before you decide.
Yes, delayed reconstruction is a routine option and many people choose it once cancer treatment is complete. The tissue available, previous radiotherapy and your general health guide which method suits you.