A tear at the inner corner of the eyelid often cuts the tiny channel that drains tears into the nose. Repairing that channel early is what keeps the eye from watering for years afterwards.
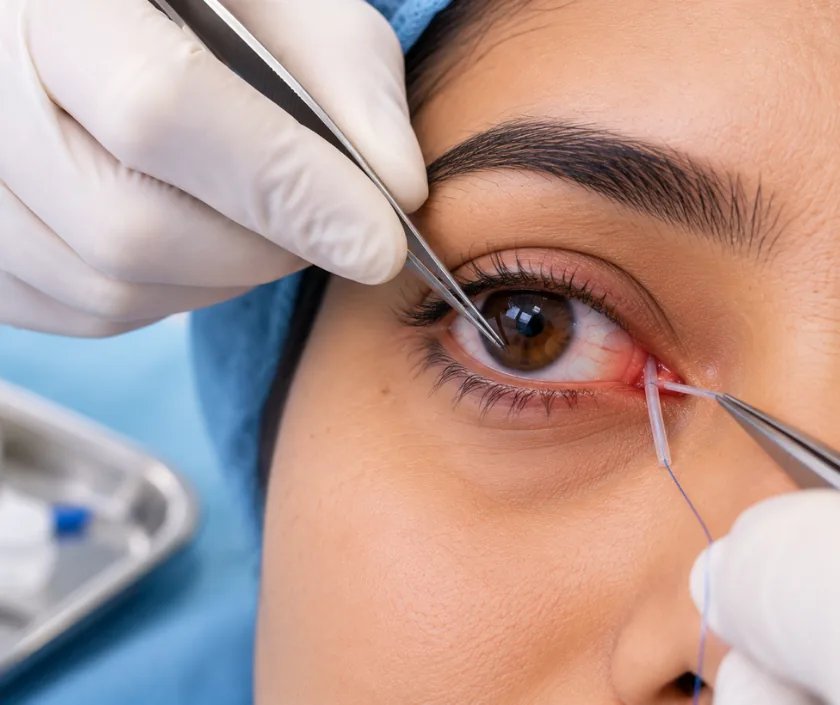
Canalicular repair is surgery to reconnect the small tear drainage channel that runs from the inner corner of the eyelid towards the nose. Cut ends are found under magnification, threaded over a soft silicone tube and stitched together. Timing matters, because a channel repaired within the first day or two heals far more reliably than one left alone.
Tears do not simply evaporate. They drain through two tiny openings at the inner edge of each eyelid into fine channels called canaliculi, which carry them to a sac beside the nose and then down into the nostril. Because these channels run just under the skin at the inner corner, a cut in that area divides them easily, even when the wound looks small.
A divided channel that is left alone tends to scar shut. Tears then have nowhere to go, and the eye waters constantly in wind, cold air and bright light. Correcting that afterwards is far harder than repairing the channel at the time, which is why an eyelid wound near the nose is treated as urgent.
During surgery the cut ends are found under magnification, a soft silicone tube is threaded through to act as a splint, and the ends are stitched together over it. Surrounding lid layers and the tendon at the inner corner are repaired at the same sitting. The tube stays for some months and is removed in clinic.
Repair is offered whenever the drainage channel has been cut and the ends can still be identified. That decision usually rests on how the wound sits and how much time has passed.
The lid is examined under good light and the tiny opening at the lid edge is checked. A fine probe or gentle irrigation shows whether the channel has been divided and at what point.
General anaesthesia is usual, since the work is slow and precise. Your surgeon cleans the wound and finds the cut ends of the channel with magnification.
A soft silicone tube is passed along the channel and down towards the nose. It acts as a splint holding the repaired channel open while healing takes place.
Fine stitches bring the cut ends together over the tube. Surrounding tendon and lid layers are then repaired so the inner corner sits in its normal position.
The tube stays in place for some months and is usually not noticed in day to day life. Removal is a quick clinic procedure once healing has settled.
The inner corner is swollen and bruised. Drops and ointment are used as advised, and the eye may water more than usual at this stage.
Bruising fades and skin stitches are removed. Your tube may be felt occasionally at the inner corner, though it should never be pulled.
Swelling has largely gone and the lid sits in its usual place. Watering is often much better, although it can still vary with wind and cold.
The tube is removed once healing has settled. Drainage is then checked in clinic to see how well the repaired channel carries tears.
Many people notice a clear improvement once the tube is removed, with tears draining normally in ordinary conditions. Some watering can still appear in cold air or wind, and a few channels narrow again despite careful repair. Where that happens, further options exist, including a second repair or an operation that creates a new drainage path. Progress is judged after the tube comes out rather than in the first weeks.
The channel being repaired is barely wider than a thread, so this work is delicate and not every repair holds. These are the problems worth knowing about beforehand.
Most of the aftercare is about protecting the tube, because it is what keeps the repaired channel open.
Watering caused by a cut drainage channel rarely settles. Once the channel scars shut, tears have nowhere to go, and correcting it later needs a bigger operation.
The drainage channel lies just under the skin at the inner corner. A short cut in the wrong place is enough to divide it completely.
Tubing of this kind is soft and sits mostly out of sight along the lid edge and inside the nose. Most people around the patient never notice it.
Delay is the main reason these repairs fail. Fresh ends can be found and joined, while older ones pull back and scar, which makes the operation harder.
Injuries at the inner corner of the eyelid are treated at Elegance Clinic in Surat with the drainage channel checked before the wound is closed, so a repairable duct is not simply stitched over.

What this repair costs depends on whether one or both drainage channels are involved, the anaesthesia used, the theatre time needed and the type of tube chosen. Removing the tube later is a short clinic visit. Because the extent of the injury is only clear once it has been examined, a written estimate is shared after assessment rather than quoted over the phone. Repair after trauma counts as reconstructive work, so most mediclaim policies cover it.
These are the questions that come up most often in consultation. If yours is not here, send it on WhatsApp and the team will reply, usually the same day.
Ask your question →The total depends on whether one or both channels are involved, the anaesthesia used and the tube chosen. Because that is only clear after examination, a written estimate is given once the injury has been assessed. Injuries of this kind are usually covered under mediclaim.
Tubing used for this purpose is soft, sits within the natural drainage path and is designed to stay for months. Some people feel it occasionally at the inner corner. Problems such as the tube slipping out or the channel narrowing again can happen and are checked at every review.
Swelling and bruising at the inner corner settle over one to two weeks, and skin stitches come out in that period. Most people return to desk work within a week. Your tube stays in place much longer and is removed at a planned clinic visit later.
Many people find watering much improved once the tube is out, with tears draining normally in ordinary conditions. Some watering can remain in wind or cold air. If the channel narrows again, further options exist, including a second repair or an operation that builds a new drainage path.
Not every one, though each has to be checked. The drainage channel lies just under the skin there, so it is probed or irrigated before the wound is closed. Repair follows when the channel is found to be divided, since closing over it stores up trouble.
Early repair gives the best chance of success, ideally within the first day or two while the cut ends can still be found and joined without tension. Later repair is still attempted, although scarring makes it harder and the outcome less reliable.
Your lid and inner corner are examined, vision is checked and the drainage channel is tested with a fine probe or gentle irrigation. You will be told what was found, what the operation involves, how long the tube stays and what the written estimate covers.
Seeing patients from across the city and beyond: read about the practice on the plastic surgeon in Surat page, or check what a written estimate covers on the costs and insurance page.
